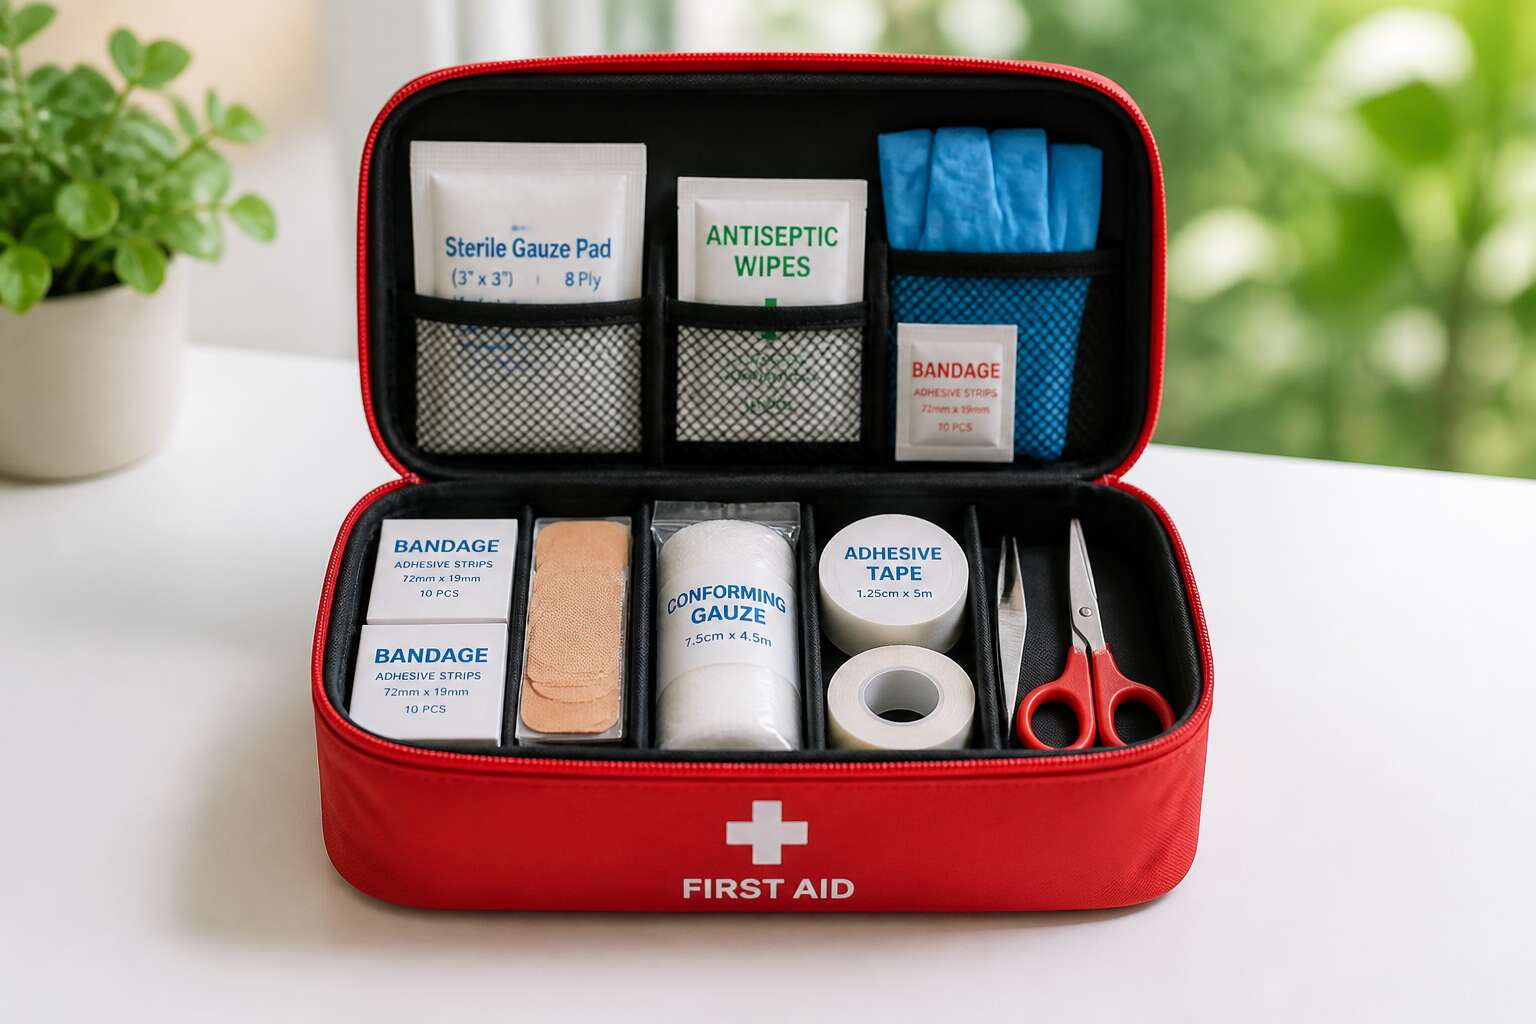
The Role of Global Health Bodies in Shaping Emergency Supply Standards
How International Health Guidelines Influence Local Compliance
When the World Health Organization revises its emergency list, a warehouse in Johannesburg feels it within months. The who first aid kit contents guidance is a baseline for insurers, auditors, and regulators.
I often see South African compliance officers discover that local standards, like SANS 10242, mirror WHO recommendations almost verbatim. Guidelines trickle down through provincial health departments into workplace manuals. A missing burn dressing can fail an audit because Geneva decided it belongs there!
Global bodies shape everyday compliance in three ways:
- WHO publishes kit lists that local authorities copy into law.
- Public sector procurement references WHO specifications.
- Training providers align coursework with WHO protocols.
Pretoria follows Geneva’s lead, then adapts. The who first aid kit contents in your clinic reflect that process.
Core Principles Behind Recommended Medical Inventories
The WHO’s model formulary, updated every few years, shapes emergency supply standards far more concretely than most managers assume. When the organization revises a medical inventory, it reviews clinical evidence from multiple continents, weighs storage constraints in remote clinics, and negotiates pricing with manufacturers. These decisions become the basis for national regulations.
Core principles behind recommended medical inventories are not random. They include:
- Selection of items that address the most common causes of injury and sudden illness
- Dosing and packaging suited to laypeople with minimal first aid training
- Shelf life considerations that account for extreme heat or humidity
The who first aid kit contents in a Johannesburg factory reflect these principles, even when local suppliers do not realize the source. Procurement officers who track who first aid kit contents know that changes are rarely arbitrary. Global bodies do not dictate every last item, but they establish the framework that national standards later mirror.
The Importance of Standardization in Crisis Response
When a mass casualty event strikes a South African township, the difference between chaos and order often comes down to whether every responder carries the same who first aid kit contents. Standardization is not bureaucratic fussiness. It is operational logic.
Global health bodies like the WHO perform a quiet function: they make emergency supplies predictable across borders. I have watched procurement teams assume their local list is unique, only to discover it mirrors a global template. A volunteer in Durban and a paramedic in Pretoria can coordinate because both work from the same reference framework. The who first aid kit contents in a municipal depot match those in a rural clinic, so training, restocking, and triage protocols align without debate.
Standardized inventories solve a recurring crisis problem:
- Supplies move across provincial lines without reprocessing
- International donations arrive with familiar specifications
- Field workers trust the kit on the shelf because they trained on the same one
A Comprehensive Breakdown of Essential Medical Accessories
Wound Care: Dressings, Bandages, and Hemostatic Agents
Wound care sits at the edge of every emergency. The difference between a controlled injury and a deteriorating one often comes down to the materials within reach. For anyone asking who first aid kit contents should prioritise, the answer begins with controlling bleeding and protecting the wound from contamination.
Dressings absorb exudate, bandages provide compression and support, and hemostatic agents accelerate clotting in severe haemorrhage. Each performs a distinct role, but they work together as a system. In South Africa, where emergency response times vary between urban and rural settings, this layered approach is essential.
- Adhesive dressings for minor cuts
- Sterile gauze pads for moderate wounds
- Pressure bandages for embedded objects
- Hemostatic gauze for arterial bleeds
Selecting the right combination requires understanding field conditions. The robust materials preferred by military units differ from what a family keeps at home. Yet the underlying logic remains unchanged: anticipate the wound types you will most likely encounter.
Cleansing and Antiseptic Supplies for Infection Prevention
In South Africa, infection is the most common complication after an emergency wound. The difference between a clean healing wound and a septic one often hinges on the antiseptic supplies you have packed. When considering who first aid kit contents should serve, cleansing agents and antiseptics form the barrier between contamination and recovery.
Antiseptic wipes, chlorhexidine solution, and sterile saline are essential. They remove debris and pathogens before a dressing ever touches the skin. Alcohol swabs work for intact skin, but they sting open wounds. Povidone-iodine offers broader antimicrobial coverage for deeper contamination.
A practical list for your kit:
– Sterile saline sachets for wound irrigation
– Chlorhexidine wipes for surrounding skin
– Povidone-iodine solution for deeper disinfection
These supplies are often overlooked in favour of dramatic trauma gear. Yet cleansing a wound properly before any bandage is applied prevents a minor injury from becoming a life-threatening infection. That is the deeper purpose of who first aid kit contents: to stop the invisible threat before it takes hold!
Diagnostic and Minor Surgical Tools: Scissors, Forceps, and Thermometers
A wound concealed by fabric is a mystery. Scissors exist to end that mystery. They cut through denim and cotton so you can see the damage beneath. Forceps handle the small intrusions: splinters, glass fragments, foreign bodies that lodge in tissue and invite infection. A thermometer measures core temperature. Fever after trauma signals sepsis before visible signs appear.
These tools deliver information. Consider who first aid kit contents must serve: a person needing certainty in a crisis. The quiet burden of any responder is deciding what is real when the evidence is incomplete. A practical list includes:
1. Trauma shears with blunt tips
2. Splinter forceps
3. Digital thermometer with probe covers
Without them you are guessing. With them you are assessing. That distinction shapes every decision that follows.
Protective Gloves and Barrier Equipment
Your hands touch the injured person before any tool does. South Africa’s HIV prevalence remains among the world’s highest, so the barrier between skin and blood is a calculation. A rescue that exposes the responder is a failed rescue. Deciding who first aid kit contents must protect begins with the person wearing the gloves.
Protective gloves have moved beyond latex. Nitrile offers superior puncture resistance and suits people allergic to latex. Pulling on a pair forces a moment of stillness.
A practical kit includes:
- Nitrile examination gloves in multiple sizes
- CPR face shield with one-way valve
- Disposable apron and splash-resistant eye protection
Gloves fail when they tear or when responders pick a size that limits dexterity. Barrier equipment also covers face shields and aprons for heavy bleeding. The question of who first aid kit contents must serve starts with the responder. Protection is the precondition for every other action!
Recommended Medications for Common Emergencies
Most households stock a first aid box, yet the question of who first aid kit contents serve becomes urgent when a child spikes a fever at 2 a.m. in a village without a pharmacy. Medicines handle what bandages cannot. Paracetamol is the primary medicine for pain and fever. Antihistamines address allergic reactions from insect bites. Oral rehydration salts are essential during summer gastroenteritis. I always add ibuprofen for inflammation and an antacid for gastric distress.
Recommended medications for common emergencies include:
- Paracetamol syrup and tablets
- Cetirizine tablets for allergies
- Oral rehydration salts
- Ibuprofen for swelling and pain
- Antacid sachets
Accessories matter too. A medication dosing card prevents guesswork. A small notebook tracks expiry dates. These additions ensure that who first aid kit contents answer to the actual household, not a generic checklist.
Adapting Your Emergency Inventory to Different Environments
Workplace Compliance and Occupational Health Requirements
Your office’s emergency inventory should not mimic a climbing expedition’s pack. In South Africa, the difference between a coastal workshop and a highveld warehouse is not trivial. The who first aid kit contents that satisfy a safety auditor in Durban may fail you in a mine near Rustenburg.
Consider these environment-specific adjustments:
- Heat-related supplies for outdoor teams
- Snakebite kits for rural sites
- Extra saline for dusty conditions
Occupational health requirements demand regular audits. I have seen compliance officers check expiry dates with religious fervour. Align who first aid kit contents with actual hazards, not the generic checklist. That is the difference between a kit that sits in a cabinet and one that saves someone’s afternoon.
Outdoor and Wilderness Expedition Essentials
A blister on the Drakensberg escarpment can turn a summit push into a rescue operation. The who first aid kit contents that serve a city office lose relevance three hours from the nearest tar road. Wilderness expeditions demand a different logic, built around weight and the reality that help will not arrive quickly.
For outdoor teams, the focus shifts to environmental threats. Sun exposure at altitude differs from the suburbs. Dehydration creeps in faster when wind and dry air accelerate fluid loss. Prioritise the veld or mountainside kit accordingly:
- Thermal blankets for shock and temperature drops
- Oral rehydration salts in single-use sachets
- Compact splinting material for fractures
- High-factor sunscreen and lip protection
The who first aid kit contents must account for carrying on your back. Every gram counts. I have packed kits for both the Kalahari and the Garden Route, and the differences are stark. Multi-use items in waterproof containers help.
Home and Multi-Person Household Considerations
A household emergency inventory morphs into a different beast once you multiply it by children and grandparents. The who first aid kit contents for a multi-person home require a spreadsheet mindset. The lone roll of bandage will vanish into a school backpack within a week.
You are stocking a micro-clinic, not a rucksack. Each resident adds a layer of complexity:
- Paediatric doses need separate packaging.
- Grandparents require their medication list on hand.
- Someone with allergies needs a spare antihistamine.
Adapting your emergency inventory to a full household is less about buying a bigger box and more about knowing who will need it at 11 pm on a Sunday.
Travel and Compact Kit Solutions
Travel changes the arithmetic of emergency preparedness. A kit that suits a living room fails in a rental car boot or an airport hold. The question of who first aid kit contents serve becomes sharper when you are far from your usual pharmacy, your usual doctor, your usual certainty.
Compact solutions demand ruthless editing. I carry only what earns its weight.
– Blister plasters for long walks
– Oral rehydration salts for unfamiliar water
– A tourniquet for remote driving
– Antiseptic wipes that double as surface cleaners
The smaller the kit, the more deliberate every choice becomes. Understanding who first aid kit contents actually protect in transit changes how you pack. A family of four on a road trip needs different supplies than a solo traveller with a carry-on. Space is the silent constraint.
Management, Maintenance, and Expiry Tracking
Systematic Checking and Expiration Management
Owning a first aid kit means accepting a quiet responsibility. The true test arrives months later, when a tube of ointment has hardened or a bandage’s wrapper has split. I schedule a three monthly review, because routine inspection protects against false confidence. Systematic checking involves more than a glance. It demands that who first aid kit contents are verified item by item, against a written inventory.
Expiration management follows a straightforward cycle. I place older stock in front and newer stock behind, which eliminates guesswork. Loaded questions about usability fade when you inspect every seal. My own approach includes:
- Discarding expired liquids and gels
- Replacing used consumables immediately
- Checking torch batteries and torch bulbs
- Confirming the inventory sheet matches reality
This discipline turns a dormant box into a dependable resource. Maintenance is not a chore; it is the thread that keeps preparation whole.
Restocking Workflows for Depleted Supplies
Managing a first aid kit inventory turns into a habit once you connect restocking to real incident patterns. I log every depletion immediately, not when the box looks empty. This workflow prevents shortages before they turn urgent.
Stockrooms need the same scrutiny as the kit itself. My replenishment routine uses a two-bin system: when the first bin empties, the second bin triggers the purchase order. Suppliers get a fixed schedule, so delivery dates stay predictable. I track three signals:
– Reorder points tied to usage rates
– Lead times from each supplier
– Batch numbers for perishable items
Expiry tracking feeds directly into restocking. Expired items exit the register the moment they leave the box. That keeps the audit trail precise and prevents misfiled entries. A current inventory sheet protects everyone who relies on who first aid kit contents.
Safe Storage Practices and Accessibility Optimization
Storage location determines whether who first aid kit contents actually get used. In South Africa, a cabinet that locks but sits close to the doorway works best for both home and workshop. Heat and humidity break down adhesive, tape, and antiseptic wipes, so keep the box away from bathrooms and direct sun. I store mine in a cool hall cupboard, mounted at adult height, out of small children’s reach.
Maintenance covers the container, not just the contents. I check the latch, hinges, and lid seal every quarter. A cracked box lets dust and insects in. Label the front with a bright cross and the last check date. Access matters too. If responders must hunt through a packed drawer, the inventory becomes decoration. A visible, labelled kit near the action wins. That access saves real time!
The Role of Training and Mock Drills in Preparedness
Expiry tracking determines whether a first aid kit works when needed. I record every item’s date when it enters the box and revisit that list monthly. A simple table inside the lid works. The real question is who first aid kit contents are meant to protect. One person must own that duty. In my household, I do. In a workplace, it should be a named employee with a backup.
Training gives the inventory meaning. A mock drill reveals gaps faster than any checklist. I once staged a burn scenario and discovered my gloves were the wrong size. Practice exposes flaws that paperwork misses.
Maintenance covers the whole system, from seals and latches to packaging dates. Rotate stock before expiry and keep the box easy to reach. A quarterly review keeps the kit trustworthy.



0 Comments